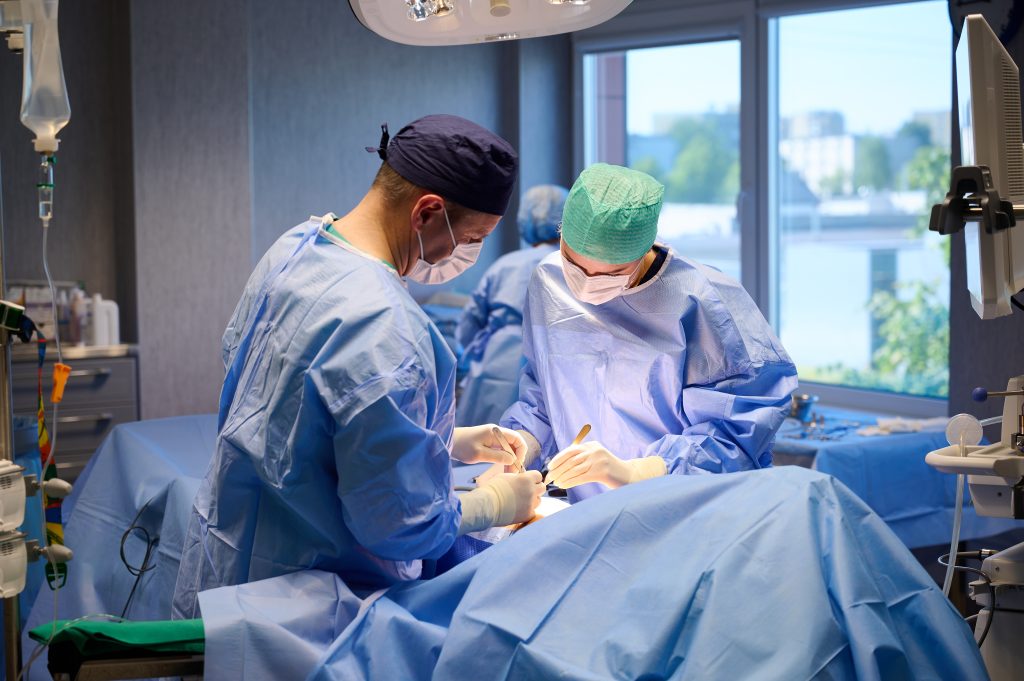
About us

Holistic approach & personalised care

NEWMAN Aesthetic Clinic is an accredited personal health care establishment providing licensed services of general as well as plastic and reconstructive surgery. The patients here can find experienced professionals of certain area applying holistic approach to healthy handsome body and well-being. Because of high quality services, holistic and individual approach to the patient the clinic is popular among the patients from all around Lithuania and other countries worldwide. The Clinic is established in Kaunas, in the centre of Lithuania and has convenient connections with other cities as well as with Vilnius and Kaunas airports.

Feel yourself

The team of NEWMAN Aesthetic Clinic is united by a general objective – to help each of our patients to feel better and finally to enjoy their own appearance. We strive for the same as you do – to feel yourself  in your body as good as possible and to have your appearance reflecting your true nature – vigorous, balanced and self-confident personality.

The case of each patient is exceptional

We understand and care about the link between the individual’s health, better quality of life, happiness and self-confidence. Therefore we consider not only the medical aspects of the plastic and reconstructive surgery. For us it is very important to listen to the patient and to understand their expectations and objectives. From the first contact we will make our best in allocating our time to understand your individual needs. Careful listening, attention to details and the advanced technologies allow us to develop the surgery and treatment plan that in the best way suits your expectations. 

Initiate the changes right now

For us it is very important that physical changes would follow favourable emotional well-being. Your safety, responsibility, respectfulness and single – mindedness are inseparable values of our everyday work. From the first contact with you our team is ready to answer all your questions.

Have you decided to say “good buy” to you body features that make you unhappy and complicate you everyday life? Contact us and we together will arrange your first individual consultation with the surgeon. During the consultation we will discuss your history, your concerns and expectations and will answer all your questions you may have.

Consult us

Application form for plastic surgery

"*" indicates required fields

General information

Hidden
Hidden
MM slash DD slash YYYY
Hidden
Hidden
Hidden

Past and present medical conditions

Heart and vascular system (Blood pressure / myocardial infarction / heart failure / angina pectioris, etc.)*
Respiratory system (pneumonia / Chronic bronchitis / pulmonary tuberculosis, etc.)*
Do you have varicose veins?*
Have you ever had thrombosis or thromboembolism?*
Liver, biliary system (liver infammation / liver cirrhosis / tumors / bile duct stones / gall bladder inflammation, etc.)*
Digestive system (stomach ulcer / inflammation / gastroesphageal reflux disease and others)*
The urinary system (kidney inflammation / swelling / inflammation of the bladder, etc.)*
Internal secretion system (thyroid, adrenal disease, tumours, diabetes / spleen, etc.)*
Nervous system (epilepsy / stroke / paralysis, etc.)*
Mental system (depression / eating disorder / panic attacks, etc.)*

Blood clotting system:

Does bruises occur spontaneously, as if without a cause?*
Do you bleed long after injury?*
Wound healing disorders (your wounds was ever formed abscesses, fistulas, etc.) ?*
Do you have acute or chronic infectious diseases (ex: Hepatitis, HIV, etc.)?*
Do you have autoimmune disease?*

Surgeries and anaesthesia

Have you had any previous surgeries?*
Where threre any complications during or after the surgery?*
Have you ever had anaesthesia?*
If yes, what kind of anaesthesia did you have?
Have you had any problems with anaesthesia?
Are you taking any medications?*
Are you allergic?*

If you answered yes, please write allergens:

Smoking / alcohol / drugs

Do you smoke?*

If you answered yes, please describe in more detail:

Do you drink alcohol?*
If answered yes, how often do you use alcohol? Once a:
Do you use drugs?*
Do you have any loose teeth?*

Women only

Will the surgery coincide with your menstrual period?
Is there a possibility, that you are pregnant at the moment?
Are you taking birth control pills?

Major illnesses you had

List*
Illness / Date
Treatment / Outcome
 

Previous surgeries

List*
Surgery
Reason
Date
 

Current medications

List*
Medication / How often taken
Reason
Date started
 

Your special needs during Your stay in Lithuania

Prefered type of surgery

Preffered surgery date

MM slash DD slash YYYY
Hidden
Hidden
Drop files here or
Max. file size: 64 MB.
    Consent*
    This field is for validation purposes and should be left unchanged.